

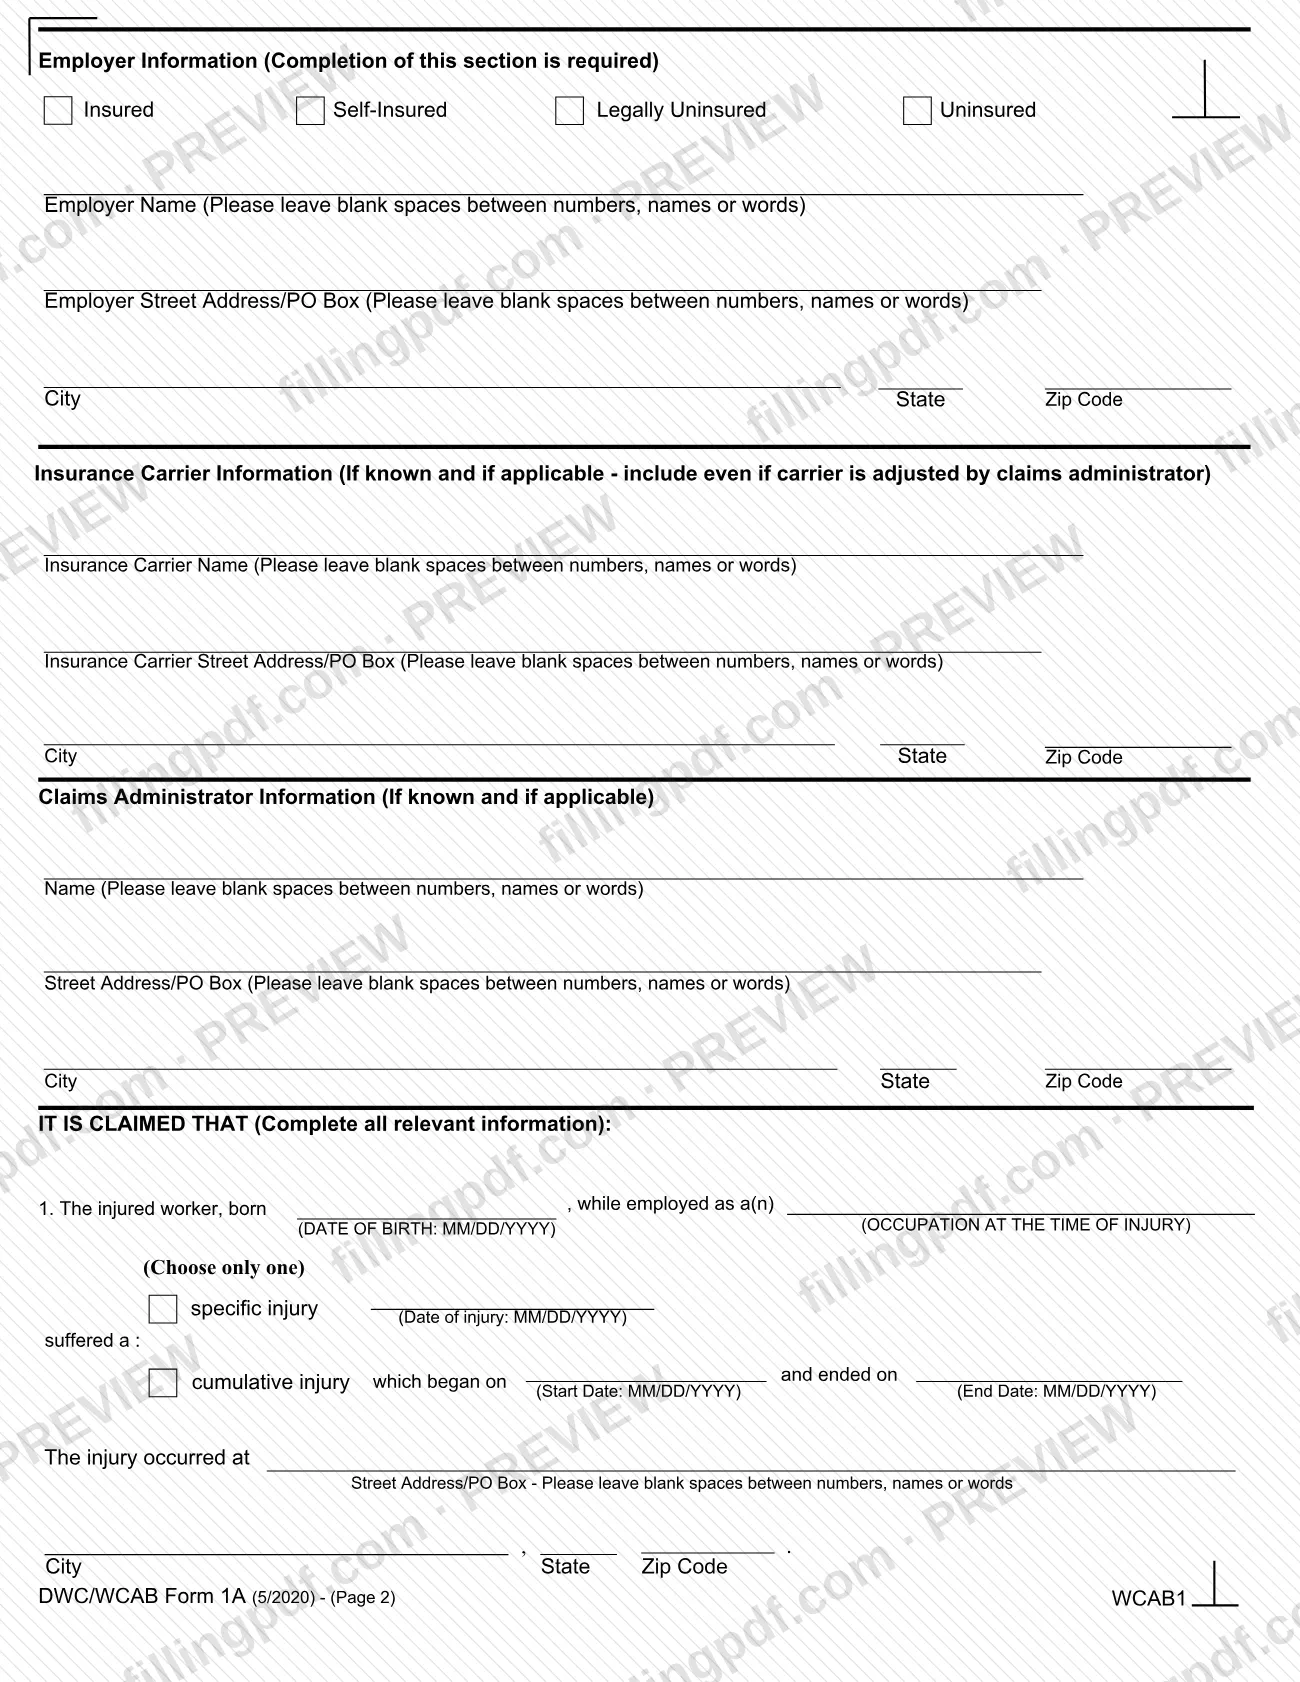




DWC/WCAB Form 1A, Application for Adjudication of Claim, is the California Division of Workers' Compensation (DWC) form that starts formal proceedings before the Workers' Compensation Appeals Board (WCAB) over a work injury claim. Many people searching for the "dwc1 form" land here because the PDF file is named DWC1.pdf; the agency lists the workers' compensation claim form separately as DWC 1. An injured worker, or in some cases a carrier, employer or lien claimant, completes it. On this page you can fill out the form online on FillingPDF and download or print the completed PDF; the original is published by the DWC at the agency's website.
Last updated
What is DWC/WCAB Form 1A?
DWC/WCAB Form 1A, Application for Adjudication of Claim, is the California form on which an industrial injury claim is presented to the Workers' Compensation Appeals Board; filing it begins formal proceedings against the defendant(s) named in the application.
The form carries the headings State of California, Division of Workers' Compensation and Workers' Compensation Appeals Board, and the revision printed on it is 5/2020. It identifies the case, the venue, the injured worker, the employer, the insurance carrier and any claims administrator. Nine numbered items then describe the claim:
- the worker's date of birth, occupation, and whether the injury was a specific or a cumulative injury, with the place of injury and the body parts hurt;
- how the injury occurred;
- actual earnings at the time of injury;
- the periods of disability;
- compensation paid;
- unemployment or state disability benefits received;
- medical treatment;
- other cases filed by the worker;
- the disagreement over liability that is the reason for the application.
A check box marks an Amended Application. The form closes with a representation block and a signature.
Do not confuse it with the form the agency's forms page lists as DWC 1, the workers' compensation claim form. This document is the application filed with the WCAB, and its instructions state that a Declaration of Readiness must be filed and served before a case can be set for hearing.
Who needs to file DWC/WCAB Form 1A?
The injured worker is the main filer: the form's first required section is the injured worker, and the claim items describe that worker's injury, earnings and treatment. The form also has an Applicant (If other than Injured Worker) block with the options Insurance Carrier, Employer and Lien Claimant, so an applicant other than the worker can be named.
Representation:
- You may be represented by an attorney or agent, or you may represent yourself. The form asks Is the Applicant Represented?
- If the answer is No, the applicant signs and dates the form.
- If the answer is Yes, the representative completes the law firm or non-attorney representative details and signs and dates it.
If any applicant is under 18 years of age, a Petition for Appointment of Guardian ad Litem must also be filed.
Anyone who needs help completing the form may ask for an information and assistance officer of the Division of Workers' Compensation. An attorney's fee is set by the WCAB when the case is decided and is ordinarily payable out of the award.
When to file DWC/WCAB Form 1A
You file the application when you are ready to begin formal proceedings against the defendant(s) over a work injury, because filing it is what starts them. Item 9 ties it to a disagreement over liability, for example for temporary or permanent disability indemnity, medical treatment or reimbursement for medical expense. The form prints no filing deadline of its own.
Use the Amended Application box when you are correcting or updating an application already on file; the venue choice must then match the original application unless an order changing venue has issued.
A hearing is a later step: the instructions say that filing and serving a Declaration of Readiness is a prerequisite to setting a case for hearing.
Documents you need
- Petition for Appointment of Guardian ad Litem, only if any applicant is under 18 years of age; the instructions say forms are available from the WCAB district office or by calling it.
- A short explanation of the place of injury, optional: it may be appended when the injury did not occur at a fixed or identifiable location or occurred outside the United States.
How to fill out DWC/WCAB Form 1A
Enter case number and amendment
If this is an amended application, check Amended Application. Enter the Case No. if one exists and the SSN as numbers only.
Choose venue and office code
In the required venue section, check the basis: county of residence of the employee, county where the injury occurred, or county of the employee's attorney's principal place of business. Then select the 3-letter office code for the place of hearing, from the Document Cover Sheet.
Complete the injured worker section
Enter first name, MI, last name and the address, leaving blank spaces between numbers, names or words. Use the international address line if it applies.
Name another applicant if needed
Only if the applicant is not the injured worker, check Insurance Carrier, Employer or Lien Claimant and enter that applicant's name and address.
Enter employer and insurer details
Check Insured, Self-Insured, Legally Uninsured or Uninsured and enter the employer's name and address. Add the insurance carrier and the claims administrator, if known and applicable.
Describe the injury in item 1
Enter the date of birth (MM/DD/YYYY) and occupation at the time of injury. Choose only one: specific injury with its date, or cumulative injury with start and end dates. Add the street address or P.O. Box where it occurred and up to four body parts plus other body parts.
Explain how it happened in item 2
State what the worker was doing at the time of injury and how the injury occurred.
Enter earnings and disability in items 3 and 4
Enter the monthly, weekly or hourly rate of pay, the value of tips, meals, lodging or other advantages regularly received, and hours worked per week. Give the last day off work and up to two periods of disability, dates in MM/DD/YYYY.
Answer compensation and benefits in items 5 and 6
Say whether compensation was paid; if so, give the total paid, weekly rate(s) and date of last payment. Answer Yes or No on unemployment or state disability benefits since the injury.
Complete treatment and other cases in items 7 and 8
Answer the treatment questions, including who furnished or paid for care and whether Medi-Cal paid. List doctors, hospitals or clinics not provided or paid for by the employer or carrier, and up to four other case numbers.
Mark the disagreement in item 9
Check each liability dispute that applies, such as temporary disability indemnity, medical treatment or rehabilitation, or enter an item under Other (Specify).
Complete representation, sign and download
Answer Is the Applicant Represented? If Yes, the attorney or representative fills in the firm and contact details. Sign, enter city and MM/DD/YYYY date, check every section, then download or print the completed PDF from FillingPDF.
How to submit DWC/WCAB Form 1A
The form is filed with the Workers' Compensation Appeals Board (WCAB), named in its heading; it prints no mailing address, portal or fee, so use the WCAB office for the venue you selected.
- Venue and office: The form requires you to choose the basis of venue and to select the 3-letter office code for the place of hearing, taken from the Document Cover Sheet.
- Service if you have an attorney or agent: Your attorney or agent serves all documents under Labor Code section 5501 and the WCAB's Rules of Practice and Procedure.
- Service if you have none: The WCAB serves copies of this application on all parties. If you file any other document, you must mail or deliver a copy to all parties in the case.
- Help: You may request an information and assistance officer of the Division of Workers' Compensation.
- Minors: The Petition for Appointment of Guardian ad Litem forms are available from the district office of the WCAB or by calling it.
FillingPDF lets you fill out and download the PDF; submission follows the channels above.
Common mistakes to avoid
- Leaving blank a section marked "Completion of this section is required": venue choice, injured worker and employer information.
- Choosing a different venue on an amended application; the instructions require the same venue as the original unless an order changing venue has issued.
- Entering no street or P.O. Box address for the place of injury; for an injury with no fixed location, or outside the United States, use the employer's business address or another appropriate address.
- Checking both injury types in item 1; the form says to choose only one, specific injury (one date) or cumulative injury (start and end dates).
- Not specifying Medi-Cal, Medicare, group health insurance or a private carrier when one paid for medical treatment.
- Filing for a worker under 18 without the Petition for Appointment of Guardian ad Litem.
- Leaving the form unsigned: the applicant signs if not represented, and the representative signs if represented.
- Not sending copies of any later document you file to all parties when you have no attorney or agent.
- Treating this application as the DWC 1 workers' compensation claim form that the agency lists separately.
Frequently asked questions
What is the DWC1 form Application for Adjudication of Claim?
It is DWC/WCAB Form 1A, the form that begins formal proceedings before the California Workers' Compensation Appeals Board against the defendant(s) you name. The PDF file is named DWC1.pdf, which is why people search for it as the dwc1 form.
Is this the same as the DWC 1 workers' compensation claim form?
No. The DWC forms page lists the workers' compensation claim form separately as DWC 1, under employer forms. This page is the Application for Adjudication of Claim, DWC/WCAB Form 1A, which is addressed to the WCAB.
Do I need an attorney to file an Application for Adjudication of Claim?
No. The instructions say you may be represented by an attorney or agent, or you may represent yourself. If you are unrepresented, you sign and date the form; if represented, your representative completes and signs the representation section.
Can I fill out DWC/WCAB Form 1A online?
Yes, you can fill out the PDF online on FillingPDF and download or print it. FillingPDF is independent and does not file the application; you submit it through the WCAB channels for your venue.
Which venue do I choose on the application?
Check one basis: county of residence of the employee, county where the injury occurred, or county of the employee's attorney's principal place of business. Each cites Labor Code section 5501.5. Then select the 3-letter office code from the Document Cover Sheet.
What if the injury had no fixed location?
You must still enter a U.S. street or P.O. Box address for the place of injury. Use the employer's business address or another appropriate address, and you may append a short explanation of where the injury happened.
What if the injured worker is under 18?
A Petition for Appointment of Guardian ad Litem must be filed. The instructions say the forms are available from the district office of the Workers' Compensation Appeals Board, or you can call the office and request one.
Who serves the application on the other parties?
If you have an attorney or agent, that person serves all documents under Labor Code section 5501. If you have none, the WCAB serves copies of this application on all parties; you must mail or deliver any other document you file to all parties.
Ready to fill out DWC/WCAB Form 1A?
Fill out DWC/WCAB Form 1A now