
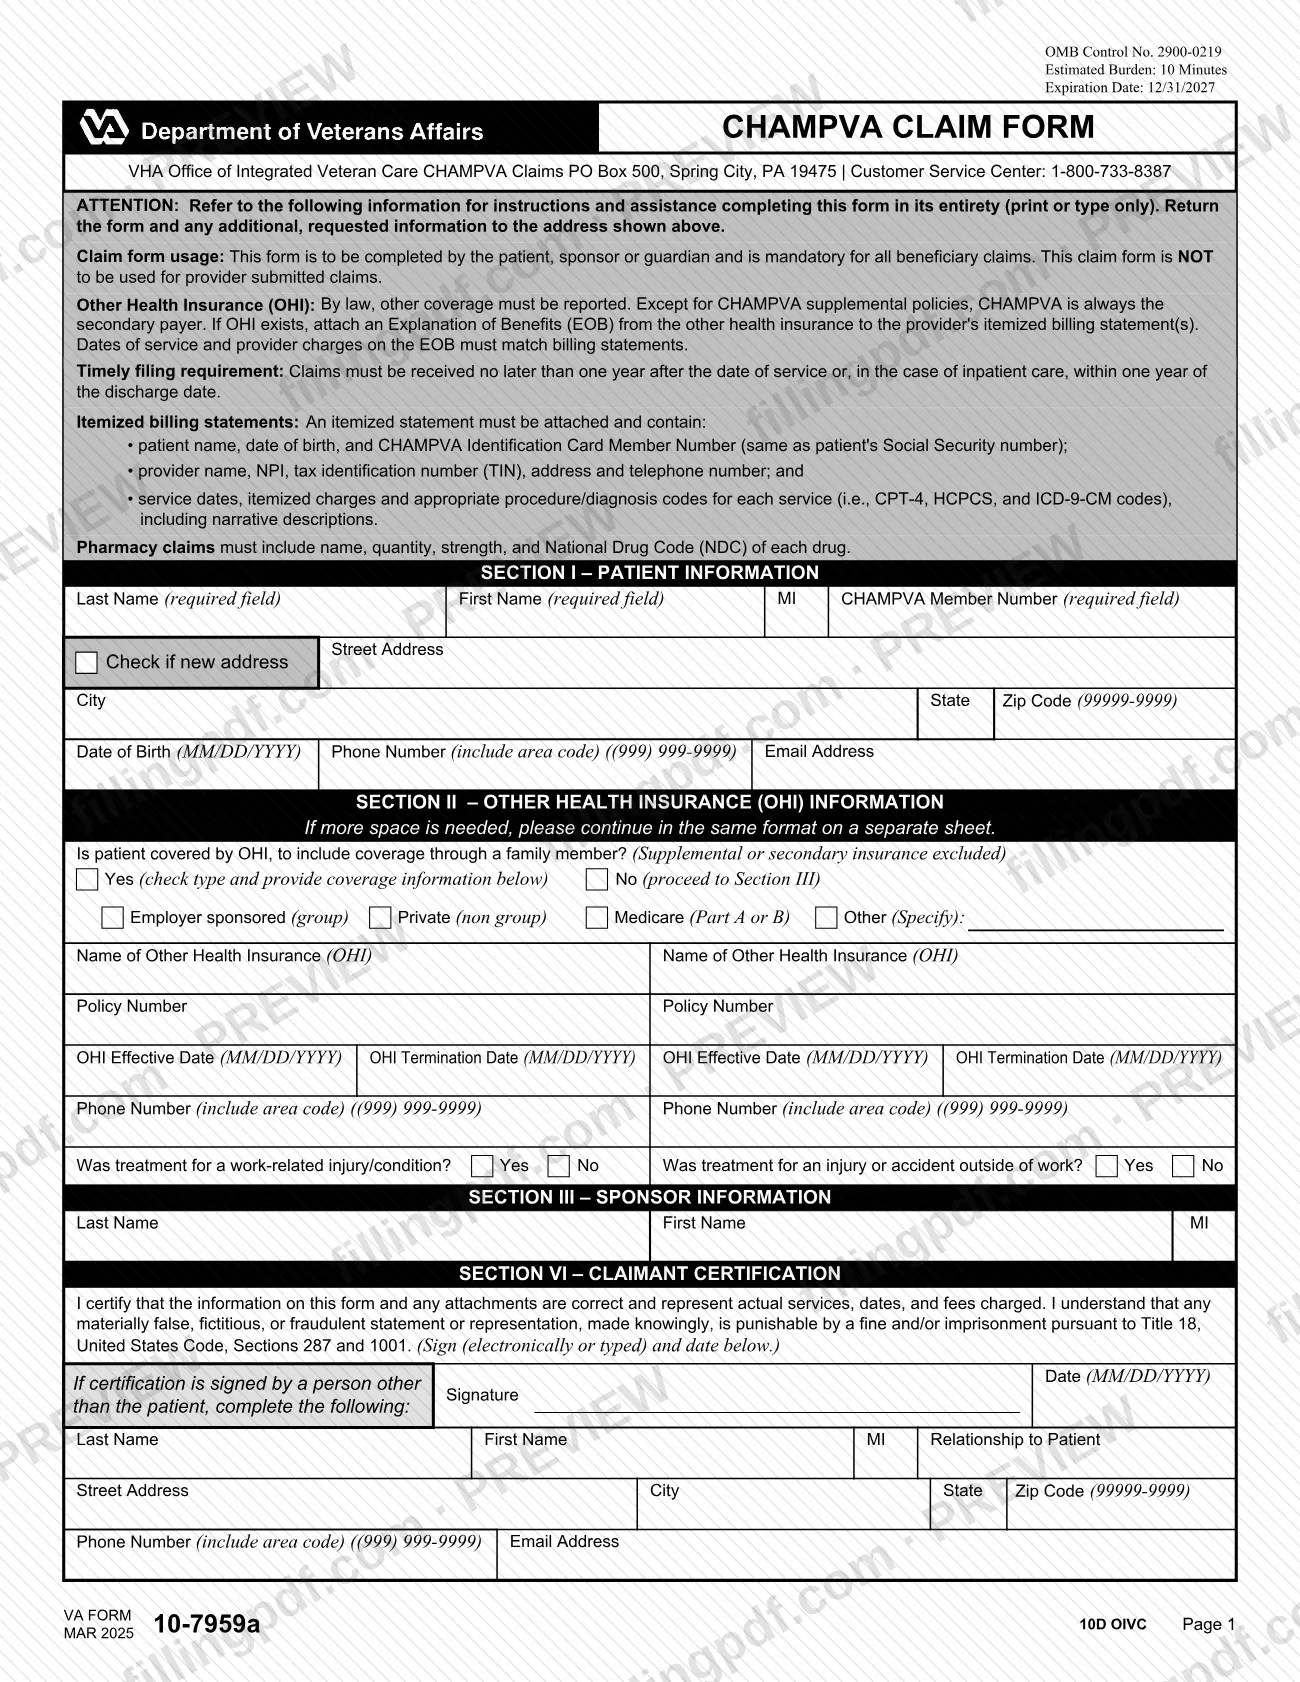

Form 10-7959a, the CHAMPVA Claim Form, is the paper claim that the U.S. Department of Veterans Affairs (VA), Veterans Health Administration, uses for reimbursement claims from people enrolled in the Civilian Health and Medical Program of the Department of Veterans Affairs (CHAMPVA). The patient, sponsor or guardian completes it, and it is also used to send more documents for a claim already filed. On FillingPDF you can fill out the form online and download or print the completed PDF; the original form is published by the VA, and the claim goes to the VA through its own channels.
Last updated
What is 10-7959a?
Form 10-7959a, CHAMPVA Claim Form, is the VA form on which a CHAMPVA beneficiary, sponsor or guardian claims reimbursement for medical care. The form states that it is mandatory for all beneficiary claims.
The form is issued by the VHA Office of Integrated Veteran Care and carries OMB Control No. 2900-0219. It has sections for patient information (Section I), other health insurance (Section II), sponsor information (Section III) and a claimant certification (Section VI). The certification is signed under a warning that a materially false, fictitious or fraudulent statement is punishable under Title 18, United States Code, Sections 287 and 1001.
The claim form does not stand alone. An itemized billing statement must be attached, and if the patient has other health insurance (OHI), an Explanation of Benefits (EOB) from that insurer must accompany the provider's statement. By law, other coverage must be reported, and except for CHAMPVA supplemental policies, CHAMPVA is always the secondary payer.
The form is not for provider-submitted claims. VA.gov describes it as the form to use if you are currently enrolled in CHAMPVA and want to file a claim for reimbursement, or if you need to submit more documents for a claim you already filed. VA.gov also offers an online tool for filing the claim instead of the paper form.
Who needs to file 10-7959a?
The patient, the sponsor or a guardian completes Form 10-7959a when a CHAMPVA beneficiary files a claim. VA.gov says to use it if you are currently enrolled in CHAMPVA and want reimbursement, or if you must send additional documents for a claim you already filed.
- Beneficiaries and their sponsors or guardians: the form is mandatory for all beneficiary claims.
- Someone signing for the patient: if the certification is signed by a person other than the patient, that person completes the section giving name, relationship to the patient, address, phone number and email address.
- Patients with other health insurance: report it in Section II, including coverage through a family member. Supplemental or secondary insurance is excluded from that question.
Do not use this form for provider-submitted claims. The form states that it is not for them.
The form also warns that divorce or annulment of the marriage to the qualifying sponsor ends CHAMPVA eligibility at midnight on the effective date of the dissolution. Report changes in status immediately to CHAMPVA.
When to file 10-7959a
Claims must be received no later than one year after the date of service. For inpatient care, the claim must be received within one year of the discharge date. Plan your mailing so it arrives within that period, because the rule is based on receipt.
The form also serves as the way to send additional requested information for a claim already filed, according to VA.gov. No other deadline is printed on the form. Changes in status, such as the end of a marriage to the sponsor, are to be reported to CHAMPVA immediately rather than on this claim form.
Documents you need
- An itemized billing statement from the provider, showing the patient name, date of birth and CHAMPVA Identification Card Member Number (the same as the patient's Social Security number).
- On that statement: the provider name, NPI, tax identification number (TIN), address and telephone number.
- On that statement: service dates, itemized charges and the appropriate procedure and diagnosis codes for each service (CPT-4, HCPCS and ICD-9-CM codes), with narrative descriptions.
- An Explanation of Benefits (EOB) from the other health insurance, attached to the provider's itemized billing statements, only if the patient has OHI. Dates of service and charges on the EOB must match the billing statements.
- For pharmacy claims: the name, quantity, strength and National Drug Code (NDC) of each drug.
- A separate sheet in the same format, only if you need more space for other health insurance information.
How to fill out 10-7959a
Gather your billing statements
Collect the provider's itemized billing statement for each service and, if the patient has other health insurance, the insurer's EOB. The form says to print or type only.
Enter patient information
In Section I, enter the last name, first name, middle initial and CHAMPVA member number, which are marked required, then the street address, city, state and ZIP code (99999-9999). Add the date of birth as MM/DD/YYYY, a phone number with area code and an email address.
Mark a new address
Check Check if new address in Section I if the address differs from the one CHAMPVA has on file.
Answer the other health insurance question
In Section II, check Yes or No to whether the patient is covered by OHI, including coverage through a family member; supplemental or secondary insurance is excluded. If No, go to Section III.
List each other insurance plan
If Yes, check the type: employer sponsored (group), private (non group), Medicare (Part A or B) or other (specify). Enter the plan name, policy number, effective and termination dates as MM/DD/YYYY, and a phone number. Use a separate sheet in the same format if you need more space.
Answer the injury questions
In Section II, check Yes or No for whether treatment was for a work-related injury or condition, and whether it was for an injury or accident outside of work.
Enter sponsor information
In Section III, enter the sponsor's last name, first name and middle initial.
Complete any remaining sections
Fill in any other sections printed between Section III and Section VI, following the labels on the form.
Sign the claimant certification
In Section VI, sign (electronically or typed) and date as MM/DD/YYYY after reading the certification that the information and attachments are correct.
Add details if someone else signs
If a person other than the patient signs, enter that person's last name, first name, middle initial, relationship to the patient, address, phone number and email address.
Review and download the completed PDF
Check each entry against the billing statements, then download or print the completed PDF from FillingPDF and assemble it with the attachments for mailing as described under How to submit.
How to submit 10-7959a
You can file by mail with the paper form or use the VA's online claim tool.
- By mail: return the completed form and any additional requested information to VHA Office of Integrated Veteran Care CHAMPVA Claims, PO Box 500, Spring City, PA 19475. Attach the itemized billing statement and, if OHI exists, the EOB.
- Online: VA.gov says you can file a claim online instead of filling out and sending the paper form, at https://www.va.gov/family-and-caregiver-benefits/health-and-disability/champva/file-champva-claim-10-7959a/.
- Questions: call the CHAMPVA Customer Service Center or Help Line at 1-800-733-8387.
Reports of changes in status go to a different address: CHAMPVA, ATTN: VHA Office of Integrated Veteran Care CHAMPVA Eligibility, PO Box 137, Spring City, PA 19475, or by calling 1-800-733-8387. Do not send the completed form to the VA Reports Clearance Officer email address on the form; it is only for comments on the burden estimate. FillingPDF lets you fill out and download the PDF; submission follows the VA channels above.
Common mistakes to avoid
- Using Form 10-7959a for a provider-submitted claim; the form states it is not to be used for those.
- Sending the claim more than one year after the date of service, or, for inpatient care, more than one year after discharge.
- Mailing the claim without an itemized billing statement showing the provider's NPI, TIN and the procedure and diagnosis codes.
- Leaving out the EOB when the patient has other health insurance, or attaching an EOB whose dates of service and charges do not match the billing statements.
- Counting supplemental or secondary insurance as OHI in Section II; the question excludes it.
- Leaving required fields blank in Section I: last name, first name and CHAMPVA member number are marked required.
- Submitting the form unsigned or undated; Section VI must be signed (electronically or typed) and dated.
- Sending the completed form to the VA Reports Clearance Officer email address instead of the CHAMPVA Claims address.
Frequently asked questions
What is VA Form 10-7959a used for?
Form 10-7959a is the CHAMPVA Claim Form. A CHAMPVA beneficiary, sponsor or guardian uses it to claim reimbursement for care, or to send more documents for a claim already filed. The form states it is mandatory for all beneficiary claims.
Can providers use the CHAMPVA claim form 10-7959a?
No. The form states that it is not to be used for provider-submitted claims. It is completed by the patient, sponsor or guardian, who attaches the provider's itemized billing statement.
What is the deadline to file a CHAMPVA claim?
The VA must receive the claim no later than one year after the date of service. For inpatient care, it must be received within one year of the discharge date.
Where do I mail the CHAMPVA claim form?
Mail it to VHA Office of Integrated Veteran Care CHAMPVA Claims, PO Box 500, Spring City, PA 19475. For questions, call 1-800-733-8387.
Can I file a CHAMPVA claim online instead of mailing the form?
Yes. VA.gov says you can file a claim online instead of sending the paper form, using its online tool for the 10-7959a claim. You can also fill out the PDF on FillingPDF, but FillingPDF does not file it; you must mail it to the VA.
What do I attach to Form 10-7959a?
Attach an itemized billing statement with the patient and provider details, service dates, charges and codes. If the patient has other health insurance, also attach the insurer's EOB. Pharmacy claims must list each drug's name, quantity, strength and NDC.
Is CHAMPVA the primary or secondary payer?
CHAMPVA is always the secondary payer, except for CHAMPVA supplemental policies. By law, other coverage must be reported, so Section II asks about other health insurance and the EOB must be attached when it exists.
Who signs Form 10-7959a if the patient cannot?
Someone other than the patient may sign Section VI, but must then also enter their name, relationship to the patient, address, phone number and email address in the section that follows the signature line.
Ready to fill out 10-7959a?
Fill out 10-7959a now