

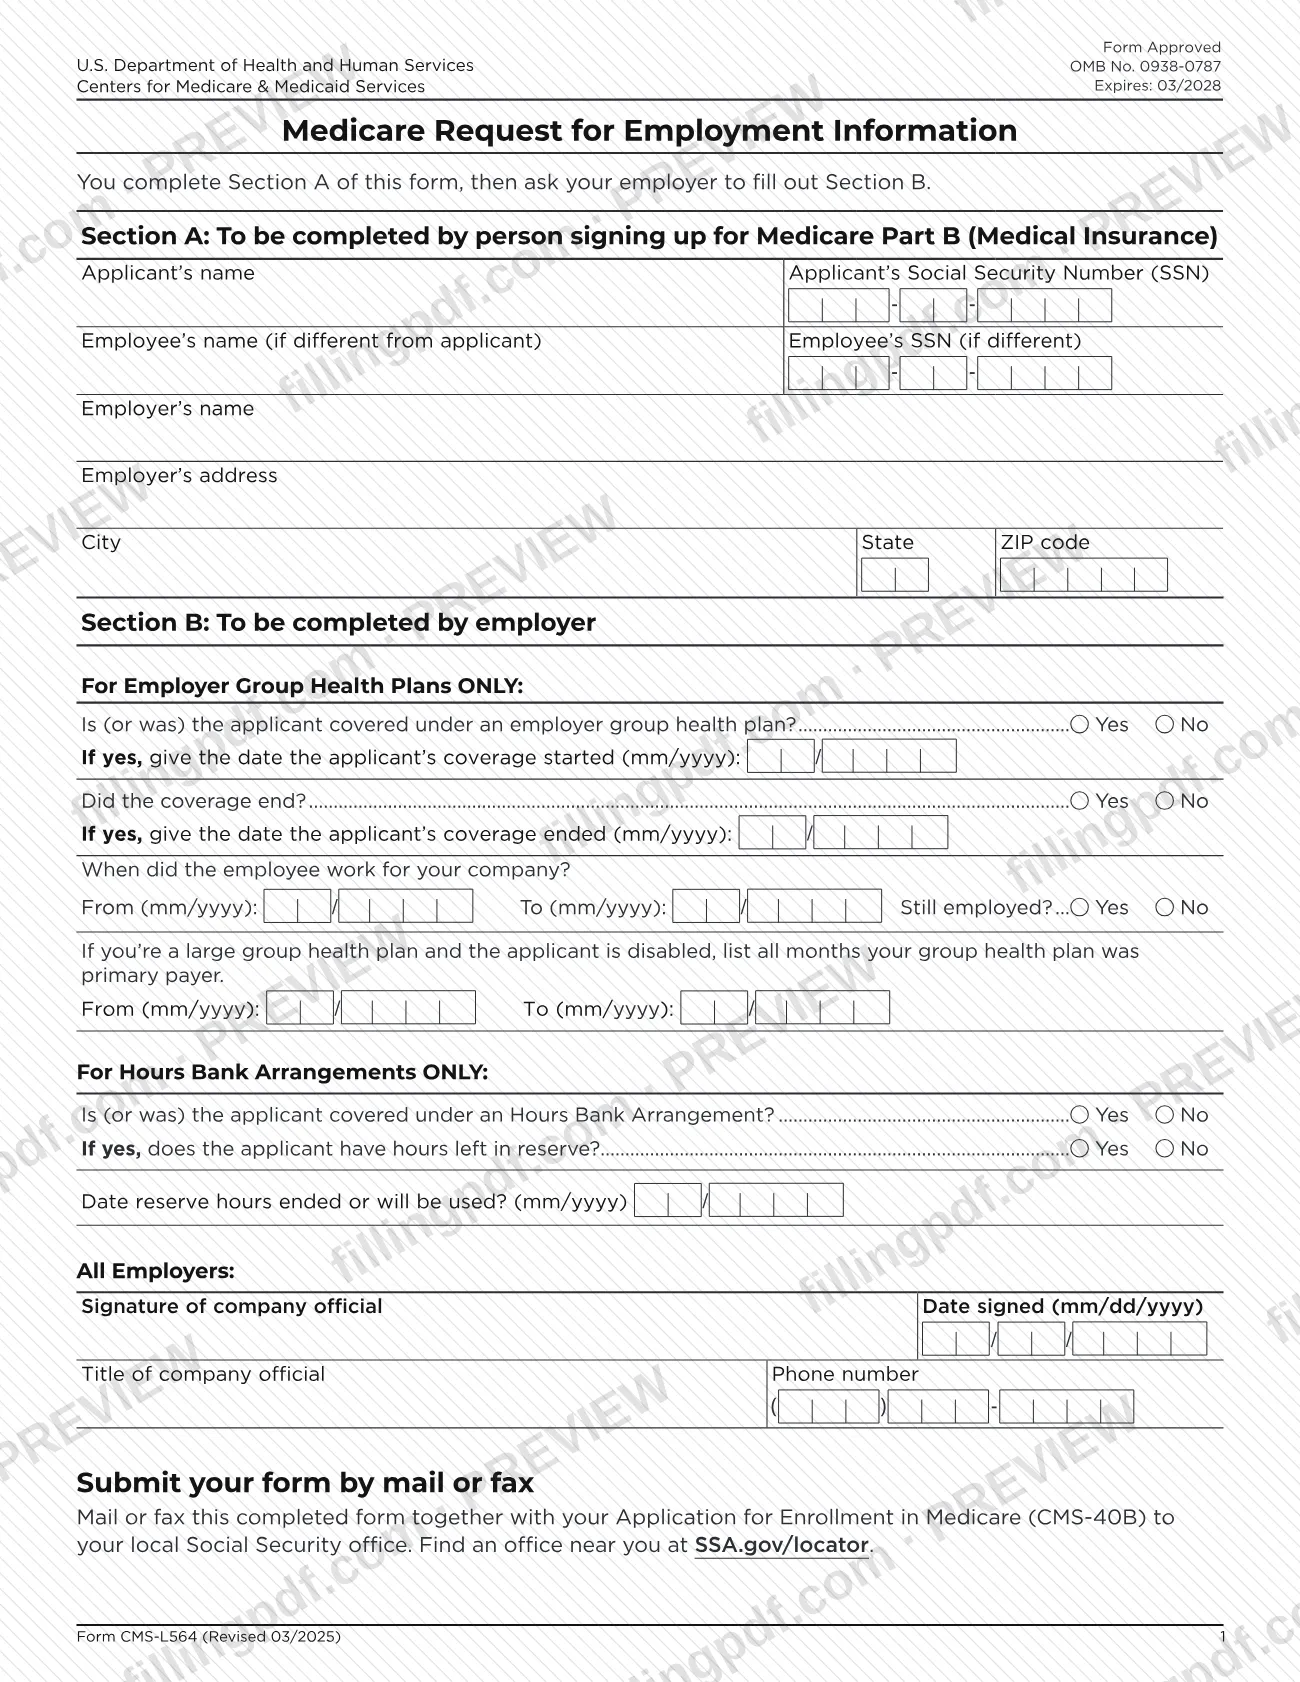
CMS-L564 is the form, printed with the title Medicare Request for Employment Information, that shows proof of group health plan coverage based on current employment so you can enroll in Medicare Part B. It is published by the Centers for Medicare & Medicaid Services (CMS). You complete Section A, your employer completes Section B, and the form goes to your local Social Security office with your Medicare enrollment application. On FillingPDF you can fill out the form online and download or print the completed PDF; the official PDF is published by CMS.
Last updated
What is CMS-L564?
Form CMS-L564, Request for Employment Information, printed on the form as Medicare Request for Employment Information, is the Centers for Medicare & Medicaid Services (CMS) form that documents group health plan coverage through current employment, so a person can enroll in Medicare Part B (Medical Insurance).
The form has two parts. In Section A, the person signing up for Part B enters the applicant's name and Social Security number (SSN), the employee's name and SSN if the employee is a different person, and the employer's name and address. In Section B, the employer reports whether the applicant is or was covered under an employer group health plan, the coverage start and end dates, and the dates the employee worked for the company.
Section B also has questions for two special cases: a large group health plan whose coverage applies to a disabled applicant, where the employer lists every month the plan was primary payer, and Hours Bank Arrangements, where the employer says whether hours remain in reserve. A company official signs and dates the form.
CMS-L564 is not an enrollment application. It travels with the Application for Enrollment in Medicare (CMS-40B). The form carries OMB No. 0938-0787, with an expiration date of 03/2028, and its Privacy Act statement says that failing to give all or part of the requested information could delay your application for enrollment.
Who needs to file CMS-L564?
You need Form CMS-L564 if you are enrolling in Medicare Part B and want to prove that you have group health plan coverage through current employment. Two situations are named on the form:
- Special Enrollment Period. You must have had group health plan coverage through your own or your spouse's current employment since the first month you were eligible for Medicare Part B. Your coverage must not have ended more than 8 months ago.
- Medicare because of a disability. You must have large group health plan coverage based on your, your spouse's or a family member's current employment.
The person signing up for Part B completes Section A. The employer, through a company official, completes Section B and signs it. Employers with an Hours Bank Arrangement answer the Hours Bank questions in Section B; employer group health plans answer the questions marked for Employer Group Health Plans ONLY.
The form does not say who may sign on the applicant's behalf. For questions about the form, it directs you to Social Security at 1-800-772-1213 (TTY 1-800-325-0778), your local Social Security office, or your State Health Insurance Program (SHIP) at shiphelp.org.
When to file CMS-L564
Submit Form CMS-L564 whenever you submit your Application for Enrollment in Medicare (CMS-40B), because the form says to mail or fax the two together to your local Social Security office. It has no separate due date of its own.
Timing rules tied to the coverage it documents appear on the form. To enroll through a Special Enrollment Period, you must have had group health plan coverage through your or your spouse's current employment since the first month you were eligible for Medicare Part B, and that coverage must not have ended more than 8 months ago. Because your employer must complete Section B before you submit, give them the form early. CMS estimates the form takes an average of 15 minutes per response to complete.
Documents you need
- Application for Enrollment in Medicare (CMS-40B): mail or fax it together with this completed form to your local Social Security office.
How to fill out CMS-L564
Confirm the form fits your situation
Use the form to show group health plan coverage based on current employment for Medicare Part B enrollment. You complete Section A, then your employer completes Section B.
Enter the applicant's name and SSN
In Section A, write the applicant's name and the applicant's Social Security Number (SSN). The applicant is the person signing up for Part B.
Add the employee's details if different
If the covered employee is not the applicant, enter the employee's name and the employee's SSN in the lines marked as different from the applicant. Otherwise leave them as the form allows.
Enter the employer's information
Write the employer's name and the employer's address, including city, state and ZIP code.
Give the form to your employer
Section B must be completed by your employer. Ask them to answer only the parts that fit their plan.
Employer reports group health plan coverage
For Employer Group Health Plans ONLY, the employer answers Yes or No on whether the applicant is or was covered and, if yes, enters the coverage start date as mm/yyyy. The employer then says whether coverage ended and, if so, gives the end date as mm/yyyy.
Employer enters employment dates
The employer gives the From (mm/yyyy) and To (mm/yyyy) dates the employee worked for the company and checks Yes or No for Still employed.
List months as primary payer if disabled
If the plan is a large group health plan and the applicant is disabled, the employer lists every month the plan was primary payer, using From and To dates in mm/yyyy.
Complete the Hours Bank section if it applies
For Hours Bank Arrangements ONLY, the employer says whether the applicant is or was covered, whether hours remain in reserve, and the date the reserve hours ended or will be used (mm/yyyy).
Have a company official sign
Under All Employers, a company official signs, enters the date signed in mm/dd/yyyy format, and gives their title and phone number.
Review and download the completed PDF
Check that both sections are complete and that the employer has signed. Download or print the completed PDF from FillingPDF, then attach it to your CMS-40B as described under How to submit.
How to submit CMS-L564
You can submit Form CMS-L564 by mail or by fax, together with your Application for Enrollment in Medicare (CMS-40B), to your local Social Security office.
- Mail or fax: send the completed form, with Section B filled out and signed by your employer, and the CMS-40B to your local Social Security office. The form gives no fax number or street address; find your office at SSA.gov/locator.
- Phone help: call Social Security at 1-800-772-1213 (TTY 1-800-325-0778). Spanish service is available at the same number by pressing 2.
- In person help: visit your local Social Security office for in-person help.
- Counseling: the State Health Insurance Program (SHIP) offers free insurance counseling at shiphelp.org.
Do not send this form or any items with your personal information to the CMS PRA Reports Clearance Officer in Baltimore. That address is only for comments on the form's accuracy or burden estimate, and items sent there are destroyed and are not forwarded to Social Security. FillingPDF lets you fill out and download the PDF; submission follows the channels above.
Common mistakes to avoid
- Submitting Form CMS-L564 alone; the form says to mail or fax it together with the Application for Enrollment in Medicare (CMS-40B).
- Filling out Section B yourself; Section B is for your employer, and a company official must sign and date it.
- Sending the form to the CMS PRA Reports Clearance Officer in Baltimore; that address is for comments only, and items sent there are destroyed.
- Applying under a Special Enrollment Period when the group health plan coverage ended more than 8 months ago.
- Entering coverage and employment dates in the wrong format; Section B asks for mm/yyyy, while the employer's signature date uses mm/dd/yyyy.
- Leaving the employee's name and SSN blank when the covered employee is a different person from the applicant, such as a spouse.
- Answering the Hours Bank questions for an ordinary employer group health plan; those questions are marked for Hours Bank Arrangements ONLY.
- Leaving out information the form asks for; the Privacy Act statement warns that this could delay your enrollment application.
Frequently asked questions
What is Form CMS-L564 used for?
CMS-L564 is the Medicare Request for Employment Information. You use it to show proof of group health plan coverage based on current employment so you can enroll in Medicare Part B. You complete Section A and your employer completes Section B.
Who fills out Section B of CMS-L564?
Your employer does. A company official completes Section B, which covers group health plan coverage dates, employment dates, and Hours Bank Arrangement questions where they apply, and then signs it with the date signed (mm/dd/yyyy), title and phone number.
Where do I send the CMS-L564 form?
Mail or fax it, together with your Application for Enrollment in Medicare (CMS-40B), to your local Social Security office. The form gives no address or fax number; find your office at SSA.gov/locator or call 1-800-772-1213.
Does my coverage have to be current to use CMS-L564?
For a Special Enrollment Period, you must have had group health plan coverage through your or your spouse's current employment since your first month of Part B eligibility, and that coverage must not have ended more than 8 months ago.
Can I use CMS-L564 if I qualify for Medicare because of a disability?
Yes, if you have large group health plan coverage based on your, your spouse's or a family member's current employment. In that case the employer lists all months the large group plan was primary payer in Section B.
Can I fill out CMS-L564 online?
You can fill out the PDF online on FillingPDF and download or print it. FillingPDF is independent of CMS and Social Security and does not submit the form; you mail or fax it to your local Social Security office.
Do I send CMS-L564 to CMS or the PRA office?
No. Send it to your local Social Security office with the CMS-40B. The CMS PRA Reports Clearance Officer address on the form is only for comments on the form, and items sent there that are not about the form will be destroyed.
What happens if the form is incomplete?
The form's Privacy Act statement says you do not have to give your information, but failing to give all or part of what is requested could delay your application for Medicare Part B enrollment.
Ready to fill out CMS-L564?
Fill out CMS-L564 now