

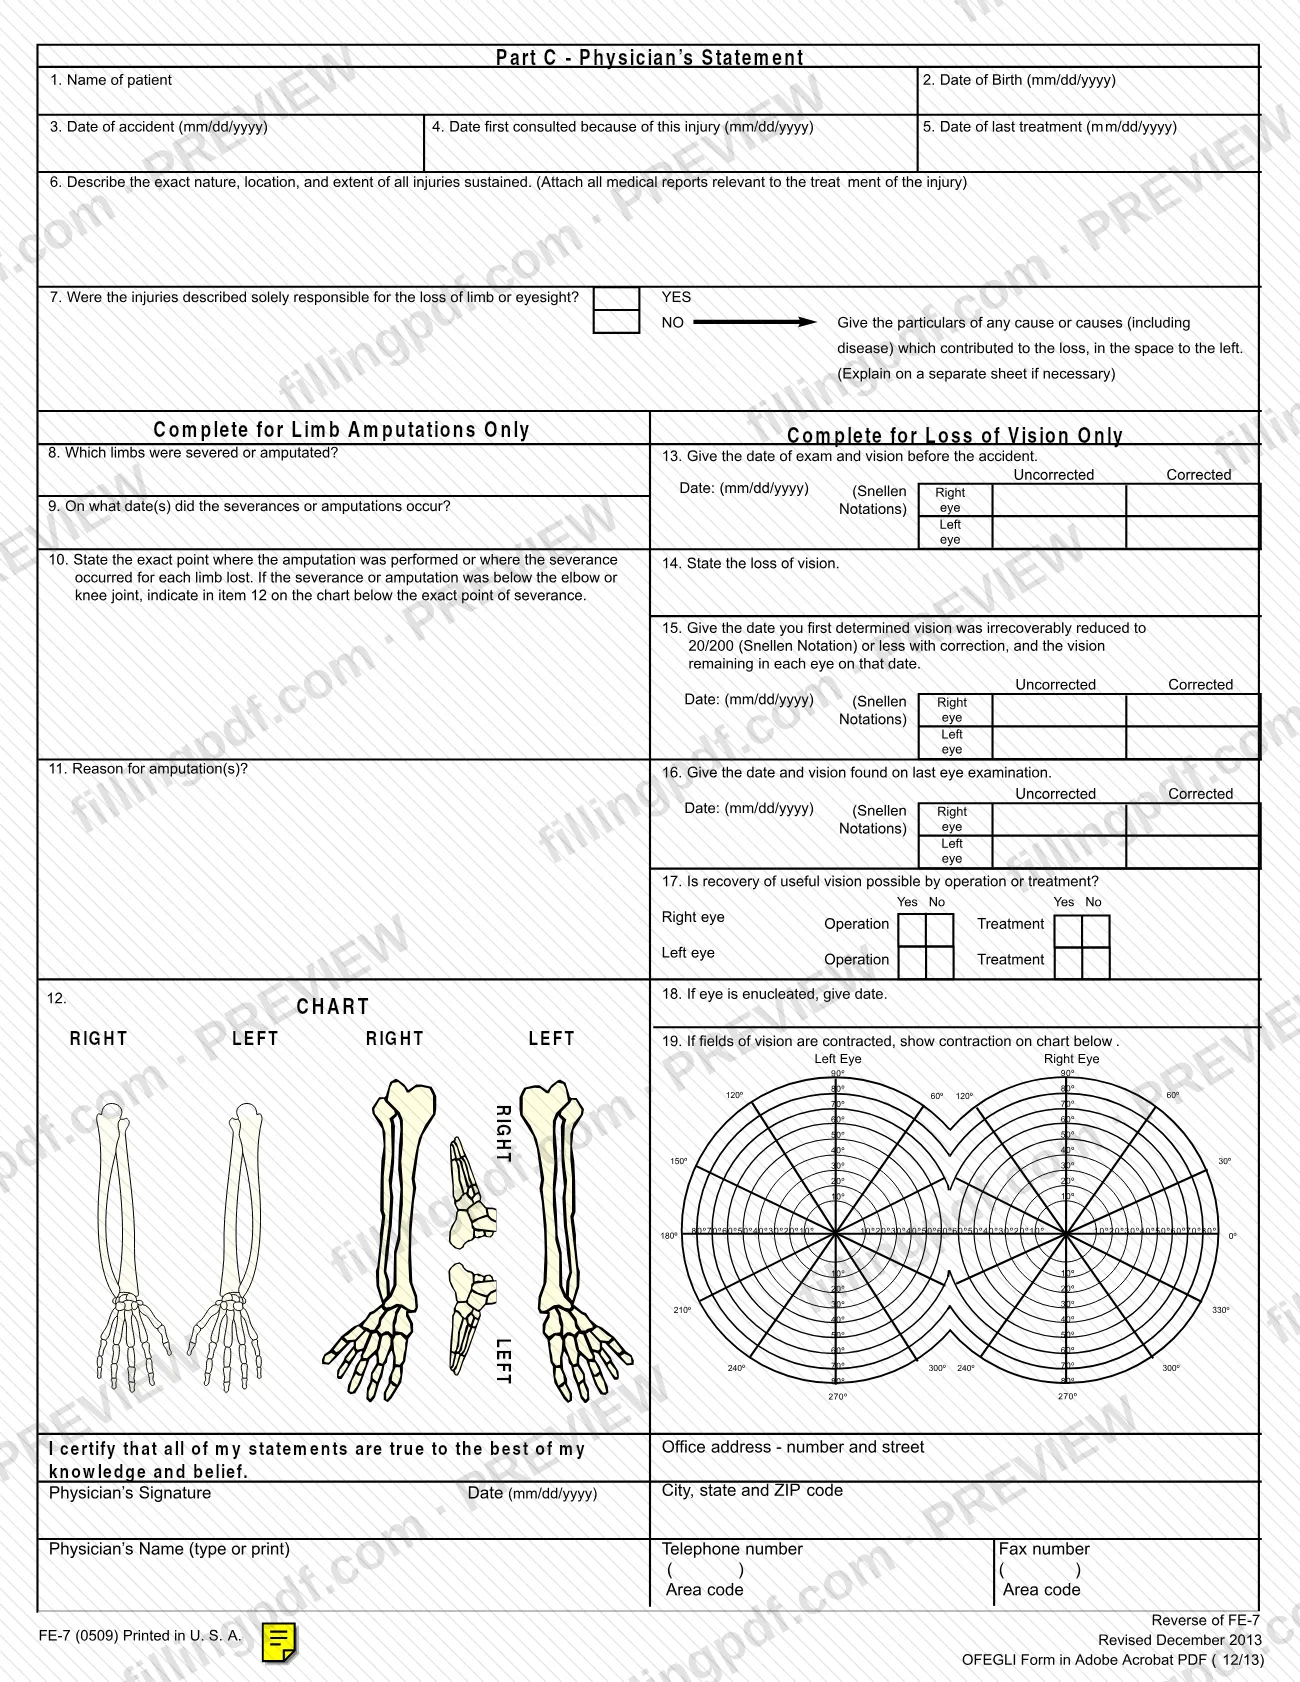
FE7, officially Form FE-7, Claim for Dismemberment Benefits, is the claim form of the Federal Employees' Group Life Insurance (FEGLI) Program, published by the U.S. Office of Personnel Management (OPM). Employees enrolled in FEGLI who lose a limb or eyesight complete Part A, the employing agency completes Part B, and a physician or other healthcare provider completes Part C. On this page you can fill out the form online on FillingPDF and download or print the completed PDF. OPM publishes the original PDF at opm.gov, and the claim itself goes to the Office of Federal Employees' Group Life Insurance (OFEGLI).
Last updated
What is FE-7?
Form FE-7, Claim for Dismemberment Benefits, is the claim form of the Federal Employees' Group Life Insurance (FEGLI) Program for an insured employee who has lost a limb or eyesight. It collects the employee's statement, the agency's certification and the physician's medical findings in one document.
The form has three parts:
- Part A, Employee's Statement: identifying details, the date and place of the accident, a brief description of it, and the employee's signed statement that the claim is true and authorizing the physician or other healthcare provider to release information.
- Part B, Agency's Certification: completed by the employing agency, which records the annual rate of basic pay for Basic Life insurance purposes on the date of the accident, whether the employee was covered by Option A that day, and certifies that the employee was covered by FEGLI.
- Part C, Physician's Statement: completed by the physician or other healthcare provider, with one section for limb amputations only and one for loss of vision only.
The form is issued by OPM and the claim is sent to the Office of Federal Employees' Group Life Insurance (OFEGLI). The printed revision is Revised December 2013, and the form warns not to use previous editions.
Who needs to file FE-7?
Employees enrolled in the FEGLI Program who lose a limb or eyesight complete this form. In the instructions, "you", "your" and "I" mean the insured employee.
Others who take part:
- Physician or other healthcare provider: completes Part C, the medical statement, and signs it.
- Employing agency: helps the employee complete the claim if necessary, completes Part B and an authorized agency official signs the certification.
- A person acting for the employee: if the employee is physically or mentally unable to complete the claim, someone else can complete it and attach a short explanation of why the employee cannot. Items 1-8 of Part A and all of Parts B and C should still be about the employee. The person completing the form signs his or her own name and gives an address and telephone number.
For help, the instructions point to your human resources office or to OFEGLI at 1-800-633-4542.
When to file FE-7
The form is completed after the accident that caused the loss of a limb or eyesight: Part A asks for the date and place of the accident, and Part C asks for the date of first consultation and of last treatment. The employee completes Part A, a physician completes Part C, and the employee then gives the form to the human resources office, which completes Part B and sends it on. The form prints no separate filing deadline, so ask your human resources office or OFEGLI at 1-800-633-4542 about timing.
Documents you need
- Copies of all medical reports from the treatment you received for the accident; the form says to attach them.
- Any police, traffic or other reports about the accident, attached to the form.
- A short written explanation of why the employee cannot complete the form, only if someone else completes it on the employee's behalf.
- A separate sheet explaining the particulars of any cause (including disease) that contributed to the loss, only if the physician needs more room than Part C, item 7 provides.
- Medical reports relevant to treatment of the injury, which the physician's statement (Part C, item 6) says to attach.
How to fill out FE-7
Confirm you have the current form
Use Form FE-7 Revised December 2013; the form says not to use previous editions. Confirm the employee is enrolled in FEGLI and has lost a limb or eyesight.
Enter identifying details in Part A
Item 1: your name (last, first, middle). Item 2: date of birth in mm/dd/yyyy. Item 3: Social Security number.
Enter employment details
Item 4: your department or agency, including bureau or division. Item 5: location of employment (city, state and ZIP code).
Describe the accident
Item 6: date of accident in mm/dd/yyyy. Item 7: place of accident (city and state). Item 8: a brief description of the accident.
Sign Part A
Sign, then enter your address, daytime and evening telephone numbers and the date (mm/dd/yyyy). By signing you state the claim is true and authorize your physician or other healthcare provider to release information about it.
Complete Part C, items 1 to 7
The physician enters the patient's name, date of birth, date of accident, date first consulted for the injury and date of last treatment, then describes the nature, location and extent of all injuries in item 6. Item 7 asks whether the injuries alone caused the loss and, if not, for any contributing causes.
Complete the limb amputation section
For limb amputations only, the physician answers items 8 to 12: which limbs were severed or amputated, the dates, the exact point of amputation, the reason, and the chart marking for a loss below the elbow or knee joint.
Complete the loss of vision section
For loss of vision only, the physician answers items 13 to 19: vision before the accident, the loss of vision, the date vision was irrecoverably reduced to 20/200 or less, the last eye examination, whether recovery is possible, any enucleation date, and any contracted fields of vision on the chart.
Have the physician sign Part C
The physician signs and dates the certification and enters his or her typed or printed name, office address, telephone number and fax number.
Pass the form to your agency for Part B
Your human resources office completes Part B: annual rate of basic pay for Basic Life insurance purposes on the accident date, Option A coverage (with the date of election if YES), and the signed agency certification.
Review, attach reports and download the PDF
Check that every item that applies is complete, then download or print the completed PDF from FillingPDF. Attach copies of medical reports and any police, traffic or other reports, and follow the channels described under How to submit.
How to submit FE-7
The employee does not mail the claim directly: the form goes through the employing agency.
- Through your human resources office: After Part A is completed and your physician or other healthcare provider has completed Part C, give the form to your human resources office. The agency completes Part B.
- Agency to OFEGLI: The agency sends the form to: Office of Federal Employees' Group Life Insurance, PO Box 6080, Scranton, PA 18505-6080.
Attach copies of all medical reports from treatment you received for the accident, and any police, traffic or other reports about it. For help, call OFEGLI at 1-800-633-4542 or contact your human resources office. FillingPDF lets you fill out and download the PDF; submission follows the channels above.
Common mistakes to avoid
- Using an older edition: the form says "Do NOT use previous" editions and prints Revised December 2013.
- Leaving Part C to the employee instead of asking a physician or other healthcare provider to complete it.
- Omitting copies of medical reports from treatment for the accident, or the police, traffic or other reports about it.
- Having someone complete the form for you without attaching a short explanation of why you cannot complete it.
- Completing both limb and vision sections of Part C: they are marked "Complete for Limb Amputations Only" and "Complete for Loss of Vision Only".
- Not giving the exact point of amputation or severance for each limb in item 10, and for a break below the elbow or knee joint, not marking it on the item 12 chart.
- Not answering Part C, item 7 about contributing causes, including disease, when the injuries were not solely responsible for the loss.
- Submitting the form without the signed Part B agency certification, or without the employee's signature in Part A or the physician's signature in Part C.
Frequently asked questions
What is Form FE-7 used for?
Form FE-7, Claim for Dismemberment Benefits, is the FEGLI claim form for an insured employee who loses a limb or eyesight. It combines the employee's statement (Part A), the agency's certification (Part B) and the physician's statement (Part C).
Who completes each part of the FE7 form?
The employee completes Part A, the employing agency completes Part B, and a physician or other healthcare provider completes Part C. If the employee cannot complete the claim, someone else can do so with a short explanation attached.
Where do I send Form FE-7?
Give the completed form to your human resources office. The agency completes Part B and sends it to the Office of Federal Employees' Group Life Insurance, PO Box 6080, Scranton, PA 18505-6080.
What do I attach to Form FE-7?
Attach copies of all medical reports from the treatment you received for the accident, plus any police, traffic or other reports about it. If someone else completes the form for you, add a short explanation of why you cannot.
Who can I call for help with the FE-7?
Contact your human resources office or call the Office of Federal Employees' Group Life Insurance (OFEGLI) at 1-800-633-4542. The employing agency is also asked to help you complete the claim form if necessary.
Can someone fill out Form FE-7 for me?
Yes, if you are physically or mentally unable to complete it. That person attaches a short explanation, signs his or her own name and gives an address and telephone number. Items 1-8 of Part A and all of Parts B and C remain about you.
Can I fill out Form FE-7 online?
You can fill out the FE-7 PDF online on FillingPDF and download or print it. FillingPDF is an independent service and does not submit the claim; it goes to OFEGLI through your agency.
Which revision of Form FE-7 should I use?
Use the edition printed Revised December 2013 (12/13), which is the version on this page. The form states "Do NOT use previous" editions.
Ready to fill out FE-7?
Fill out FE-7 now