


The Medical History Form (DOH 422-111), printed on the PDF as Birth Parent Medical History, is a Washington State Department of Health form issued through the Center for Health Statistics. A birth mother/parent or birth father/parent uses it to report medical conditions in themselves and their blood relatives, along with pregnancy and birth information. On this page you can fill out the form online on FillingPDF and download or print the completed PDF; the original PDF is published by the Department of Health at doh.wa.gov.
Last updated
What is DOH 422-111?
The Medical History Form (DOH 422-111), printed as Birth Parent Medical History, is a Washington State Department of Health form where a birth parent records medical conditions in themselves and blood relatives, plus pregnancy and birth information.
The form comes from the Center for Health Statistics, PO Box 47814, Olympia, Washington 98504-7814. The Center registers and maintains birth records for adoptees born in Washington State and for adoptees born outside the United States and adopted through a Washington State court; Chapter 26.33 RCW regulates adoption in the state.
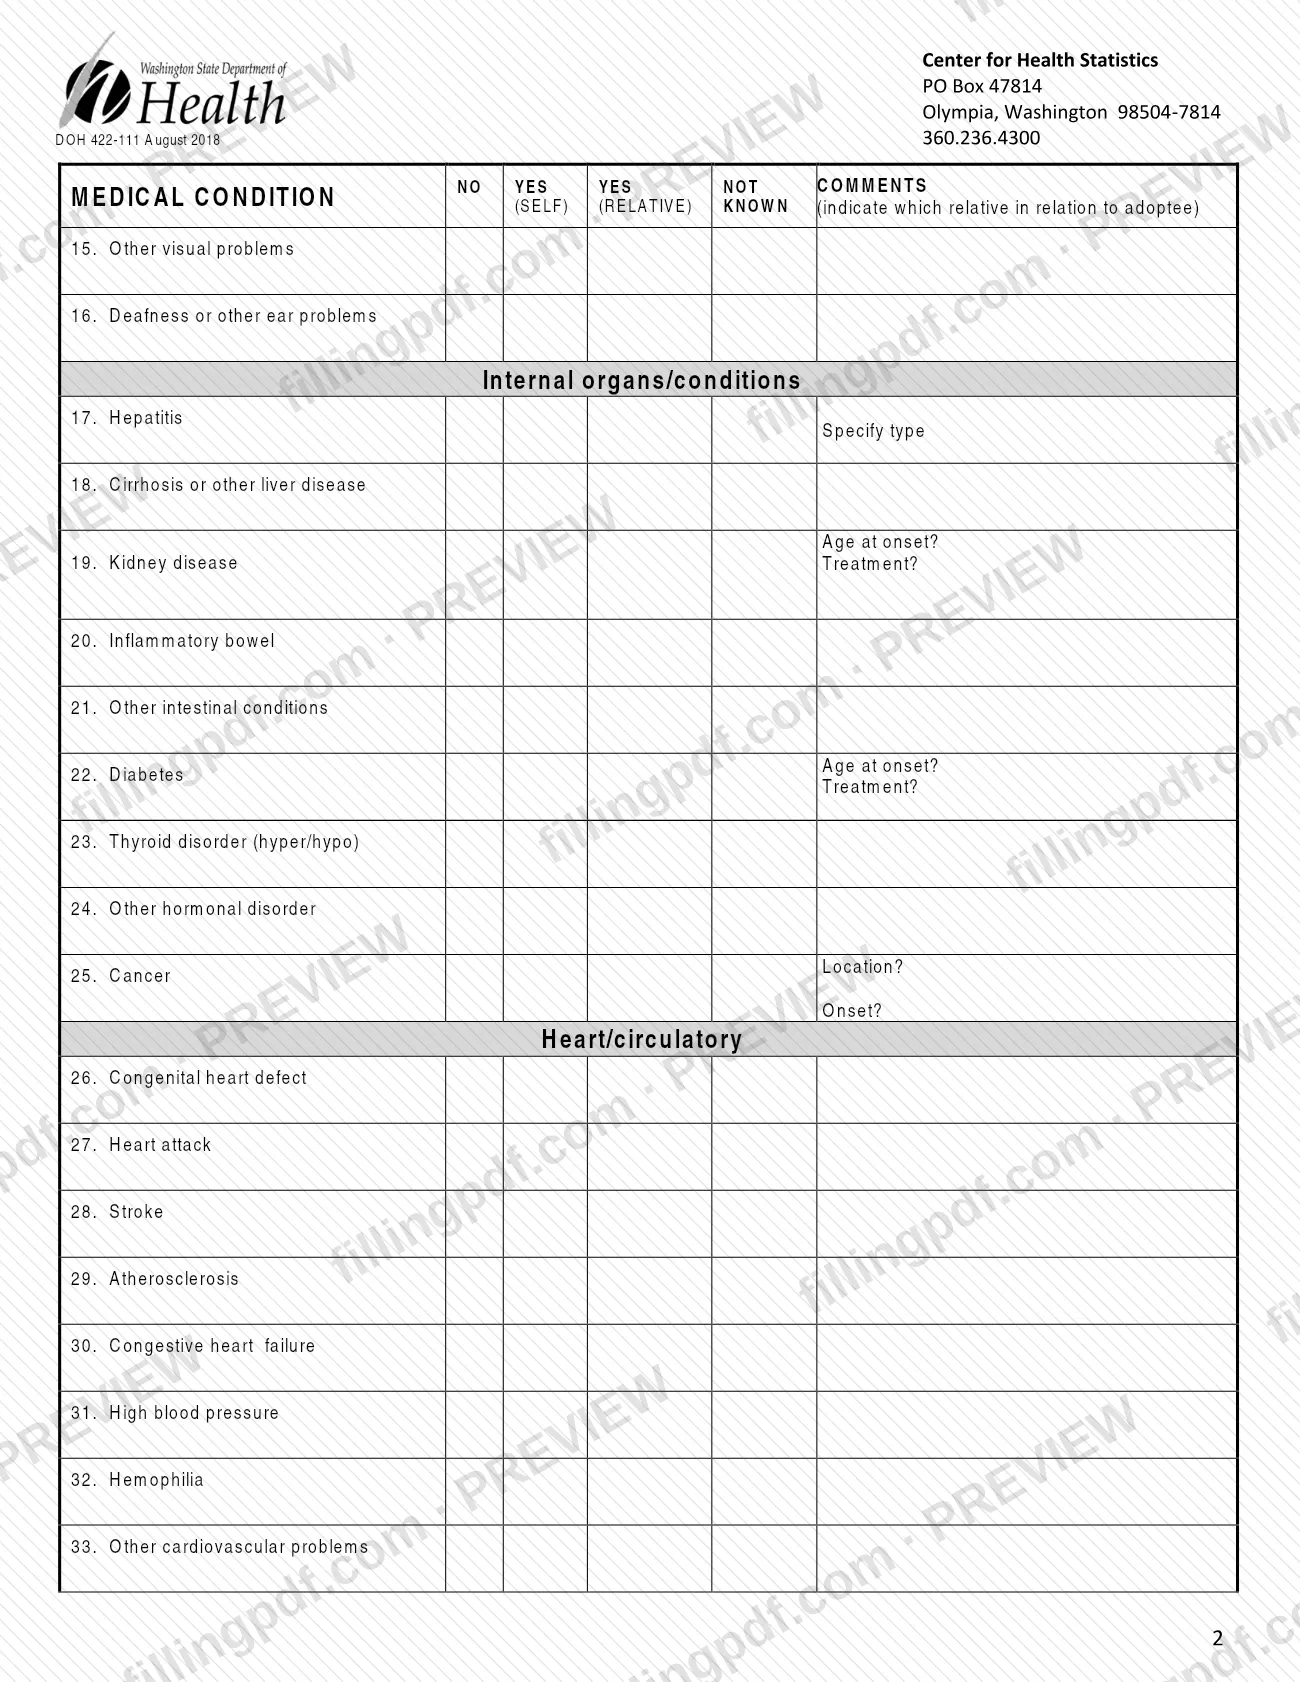
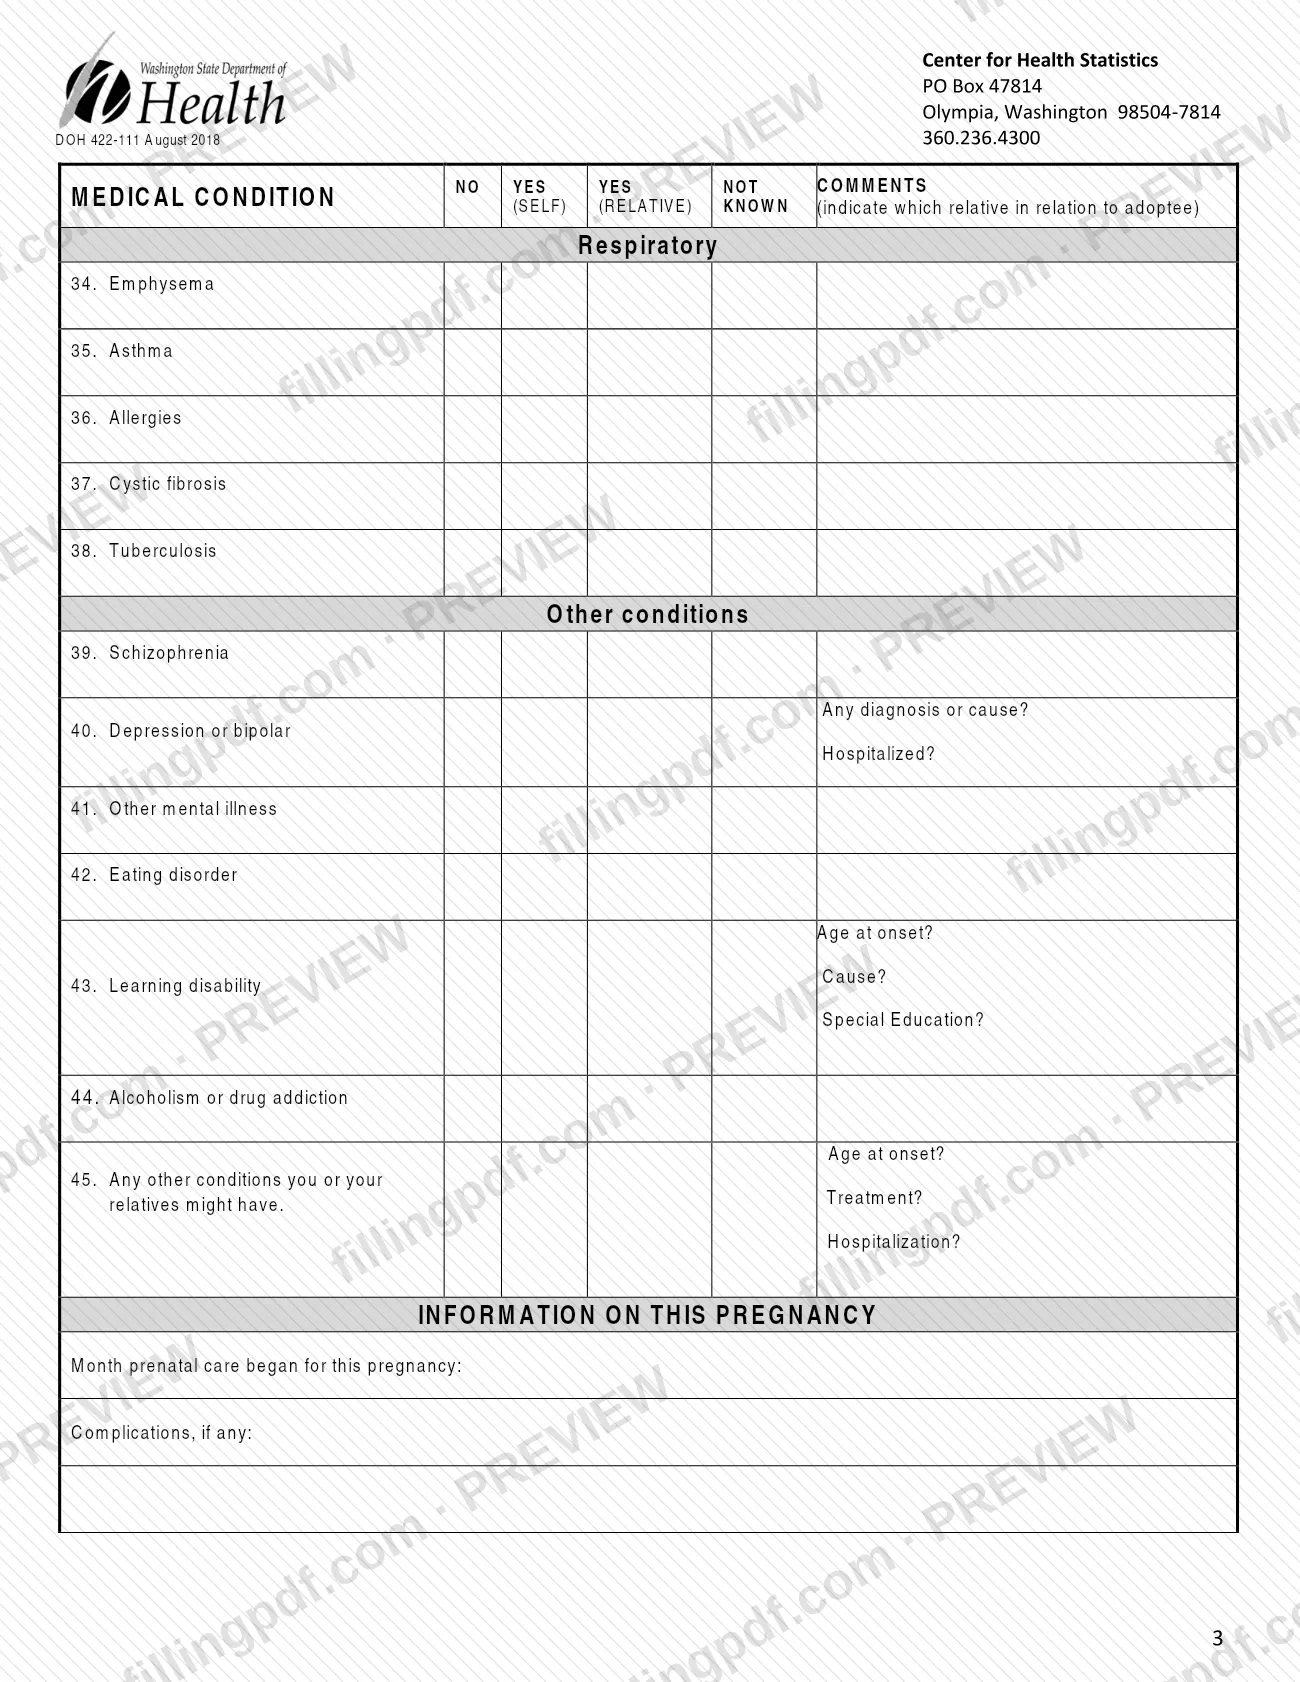
The PDF is a four-page chart of 45 numbered conditions. Each row has four columns: NO, YES (SELF), YES (RELATIVE) and NOT KNOWN, plus a COMMENTS column for naming which relative, in relation to the adoptee, has the condition. The conditions are grouped as skeletal/muscular, neuromuscular/autoimmune, visual/auditory, internal organs/conditions, heart/circulatory, respiratory and other conditions. Some rows ask follow-up questions such as age at onset, treatment or frequency.
After the chart come sections on Information on this pregnancy, Child's Birth History and an optional section, Other Information on Birth Parents.
The Center for Health Statistics lists this form under Adoption Law (SHB1525) together with the Birth Parent Contact Preference Form (DOH 422-110). The two are different documents: DOH 422-111 collects medical history, while DOH 422-110 is the contact preference form.
Who needs to file DOH 422-111?
The form is completed by a birth parent. At the top, the person completing it checks one box: Birth Mother / Parent or Birth Father / Parent.
The chart asks about two groups: you, and your blood relatives. The form lists them as your mother/parent, father/parent, sister, brother, grandparent, aunt, uncle or any other children. Answers for relatives are marked in the YES (RELATIVE) column, with the relationship to the adoptee written under COMMENTS.
The optional section, Other Information on Birth Parents, tells you to give information only as of the time of the child's birth and not to include any identifying information.
The form is not the Birth Parent Contact Preference Form (DOH 422-110), which is a separate document listed with it under Adoption Law (SHB1525). The form prints no signature block and says nothing about anyone completing it on a birth parent's behalf.
When to file DOH 422-111
Form DOH 422-111 prints no due date and names no triggering event. The Center for Health Statistics lists it with the Birth Parent Contact Preference Form (DOH 422-110) among the Adoption Law (SHB1525) materials on its adoptions page.
The form's optional section asks you to give information only as of the time of the child's birth, and the last line asks for today's date, so enter the date on which you complete the form. For questions about when the Center needs it, call the Center for Health Statistics at 360.236.4300, the number printed in the form's header.
How to fill out DOH 422-111
Check who is completing the form
Next to Person completing this form is, check Birth Mother / Parent or Birth Father / Parent.
Mark each answer in a column
For every numbered condition, check one column: NO, YES (SELF), YES (RELATIVE) or NOT KNOWN. The form tells you to indicate if information is unknown or not available.
Complete skeletal and muscular items
Answer lines 1 to 5: club foot, cleft lip or cleft palate, arthritis (osteo or rheumatoid), scoliosis or other malformations, and spina bifida.
Complete neuromuscular and autoimmune items
Answer lines 6 to 12, from muscular dystrophy to lupus. Fill in the follow-up prompts printed with these rows, such as part of body involved, age at onset, what treatment and frequency.
Complete visual and auditory items
Answer lines 13 to 16: blindness, glaucoma or other visual problems, glaucoma, other visual problems, and deafness or other ear problems.
Complete internal organ conditions
Answer lines 17 to 25, from hepatitis to cancer. Add the prompts shown, including the type of hepatitis, age at onset, treatment, location and onset.
Complete heart and circulatory items
Answer lines 26 to 33, from congenital heart defect to other cardiovascular problems, including heart attack, stroke, high blood pressure and hemophilia.
Complete respiratory and other conditions
Answer lines 34 to 38 (emphysema, asthma, allergies, cystic fibrosis, tuberculosis), then lines 39 to 45, which cover mental health, learning disability, alcoholism or drug addiction and any other conditions. Answer the prompts about diagnosis or cause, hospitalization, special education, age at onset, cause and treatment where they appear.
Use the Comments column
For every YES (RELATIVE) answer, write which relative has the condition in relation to the adoptee. If you need more space, attach a separate sheet of paper.
Describe the pregnancy
Under Information on this pregnancy, enter the month prenatal care began and any complications. Give exposure during pregnancy with the amount and frequency, and check Yes or No for alcohol and for tobacco, adding the amount and frequency.
Add birth history and optional details
Write any comments under Child's Birth History. In the optional section, give information only as of the child's birth, with no identifying information; the form then asks for the child's name on the original (pre-adoption) birth certificate, date of birth, sex (Male, Female, X or Unknown), city or county of birth and today's date.
Review and download the completed PDF
Check that every row is marked and every YES (RELATIVE) has a comment. Download or print the completed PDF from FillingPDF and deliver it as described under How to submit.
How to submit DOH 422-111
The form names no submission channel of its own: it prints no mailing instruction, portal or appointment rule. Its header identifies the issuer as the Washington State Department of Health, Center for Health Statistics, PO Box 47814, Olympia, Washington 98504-7814, telephone 360.236.4300.
The Center lists the form with the Birth Parent Contact Preference Form (DOH 422-110) under Adoption Law (SHB1525) on its adoptions page, https://doh.wa.gov/licenses-permits-and-certificates/vital-records/adoptions. Before you send or hand in the completed form, ask the Center for Health Statistics at 360.236.4300 where and how it should be delivered.
If your comments need more room than the form gives, use a separate sheet of paper, as the form allows, and keep it with the form. FillingPDF lets you fill out and download the PDF; submission follows the agency's channels.
Common mistakes to avoid
- Leaving the box at the top unchecked, so the form does not show whether a Birth Mother / Parent or a Birth Father / Parent completed it.
- Leaving a condition row blank when you do not know the answer; the form says to indicate if information is unknown or not available, using the NOT KNOWN column.
- Marking YES (RELATIVE) without writing in COMMENTS which relative has the condition in relation to the adoptee.
- Listing people who are not blood relatives; the form asks about your mother/parent, father/parent, sister, brother, grandparent, aunt, uncle or any other children.
- Skipping the follow-up prompts printed with a condition, such as age at onset, treatment, frequency or whether hospitalization was needed.
- Answering the alcohol or tobacco question Yes without giving the amount and frequency the form asks for.
- Including identifying information in the optional section; the form says not to include any.
- Giving information from a later date in the optional section instead of only as of the time of the child's birth.
Frequently asked questions
What is the Medical History Form (DOH 422-111)?
The Medical History Form (DOH 422-111), printed as Birth Parent Medical History, is a Washington State Department of Health form. A birth parent uses it to report medical conditions in themselves and blood relatives, plus pregnancy and birth information.
Who fills out Form DOH 422-111?
A birth mother/parent or birth father/parent completes it. The top of the form has a box for each, and the person completing it checks the one that applies. The form prints no signature block and names no other person who may complete it.
What if I don't know whether a relative had a condition?
Check the NOT KNOWN column for that row. The form tells you to indicate if information is unknown or not available, so every row should carry an answer rather than be left blank.
Which relatives does the medical history cover?
The form asks about you and your blood relatives: mother/parent, father/parent, sister, brother, grandparent, aunt, uncle or any other children. Mark YES (RELATIVE) and write in COMMENTS which relative, in relation to the adoptee.
Can I fill out the medical history form online?
Yes. You can fill out the DOH 422-111 PDF online on FillingPDF and download or print it. FillingPDF is an independent service and does not submit the form to the Department of Health; delivery follows the agency's channels.
Should I include identifying information on the form?
No. The optional section, Other Information on Birth Parents, says to give information only as of the time of the child's birth and not to include any identifying information. It also asks for the child's name on the original birth certificate.
How is DOH 422-111 different from DOH 422-110?
DOH 422-111 is the medical history form. DOH 422-110 is the Birth Parent Contact Preference Form. The Center for Health Statistics lists both under Adoption Law (SHB1525) on its adoptions page, but they are separate documents.
Who do I contact with questions about this form?
Call the Center for Health Statistics at 360.236.4300, the number printed in the form's header. Its mailing address in the header is PO Box 47814, Olympia, Washington 98504-7814.
Ready to fill out DOH 422-111?
Fill out DOH 422-111 now